This guide explains how www.dentalplans.com helps people evaluate dental coverage and how low-cost dental implant pathways work across English-, Spanish-, and Portuguese-speaking countries. It also compares information sources, outlines practical steps to reduce total implant costs, and provides implant-specific reference price ranges by country. The content is objective, grounded in publicly available resources.

Choosing dental implants is usually about balancing clinical suitability with affordability. For many people, the sticker shock is real: even when implants are medically appropriate, the total treatment cost can be daunting. That feeling is especially common for families planning around multiple appointments, time off work, and the reality that dental care often spans weeks or months—sometimes longer—depending on healing and prosthetic scheduling.
This guide focuses on how individuals and families can evaluate options—insurance plans, clinic selection criteria, and “low-cost” implant pathways—while keeping expectations aligned with clinical standards. Rather than treating “low-cost dental implants” as a single purchase decision, it frames affordability as a full care journey: diagnosis first, pricing second, and ongoing follow-up as non-negotiable. It also integrates the role of www.dentalplans.com in helping consumers understand dental insurance concepts and cost planning, so you can make decisions with fewer surprises.
Along the way, we’ll cover what dental implants actually cost “in practice” (not just what the implant fixture costs), what can influence overall pricing in different countries and language communities, and how to compare clinics without being misled by marketing language. You’ll also find language-specific considerations for English-, Spanish-, and Portuguese-speaking patients, because communication style and system navigation (insurance paperwork, plan networks, scheduling pathways) can affect your real out-of-pocket spending and the friction level of your care plan.
Most importantly, this guide encourages an evidence-based approach. It’s not written to argue that cheaper is always worse or that the most expensive option is always best. Instead, it emphasizes that low-cost decisions should be structured: ask for itemized estimates, confirm clinical eligibility, understand warranties, and plan for maintenance. When “low-cost” is approached this way, you can often reduce unnecessary spending while still receiving clinically appropriate treatment.
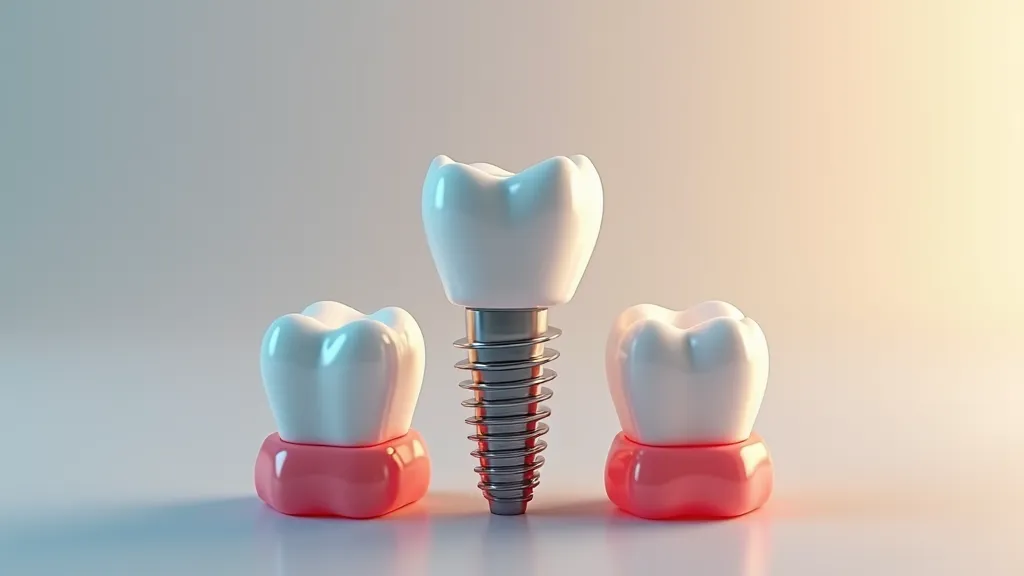
Dental implants are surgical components—often titanium or titanium alloy—placed into the jawbone. They are designed to integrate with the bone (osseointegration) and then support crowns, bridges, or dentures. A complete implant solution is typically a multi-part process:
In many real-world treatment plans, the overall cost is not only the implant fixture. It also reflects imaging and diagnostics (e.g., CBCT/3D scans), surgical expertise, bone evaluation, abutments, surgical materials, lab fees, and the final prosthetic restoration. Even post-operative visits and maintenance protocols can be priced into the “total care” package, though sometimes they are billed separately.
So when people search for “low-cost dental implants,” they are often trying to reduce one or more parts of that cost structure—without sacrificing safety or good outcomes. But because implant treatment includes multiple components, “low-cost” can mean many different things. Two people can both pay “a low price” for an implant fixture, yet end up with very different total costs and outcomes because the rest of the plan differs.
In practice, “low-cost” can be driven by one or several factors:
To make “low-cost” meaningful, it has to be connected to a clinically appropriate plan. In other words: the best value is not simply the cheapest fee—it’s the most cost-effective plan that still matches your anatomy, functional goals, and long-term maintenance needs.
Another point worth emphasizing is that the definition of “low-cost dental implants” varies. Some people mean low monthly payments (financing), while others mean low total cost. These are not always the same. A plan can have lower monthly payments but a higher overall price due to interest, fees, or longer treatment timelines. Conversely, some clinics offer lower total cost but require more upfront payment. Knowing which kind of “low-cost” you want helps you compare offers correctly.
www.dentalplans.com is relevant for readers who want to understand how dental insurance and coverage structures can influence out-of-pocket spending. Instead of focusing solely on the implant procedure price tag, coverage evaluation helps consumers plan the total care journey—for example, which pre-implant diagnostics or restorative services may be included, and how waiting periods or plan rules can affect timing.
Many patients are surprised to learn that dental insurance often does not treat implants as a simple “covered line item.” Instead, coverage may be limited by categories, waiting periods, annual maximums, and exclusions. Even when implants are not directly covered, related services (like certain diagnostics, exams, preventive care, or restorative categories) may be partially covered depending on the plan’s wording.
From an industry perspective, the practical value of insurance-related planning lies in reducing uncertainty. If you can estimate what is covered (and when), you can:
How to use a consumer insurance-planning approach: Many people benefit from using insurance education resources to understand terminology used in insurance documents. When you can interpret those documents, you ask better questions and you’re less likely to accept a quote that assumes unrealistic coverage.
Practical example of why this matters: Suppose Clinic A quotes $6,000 for an implant case and assumes no insurance. Clinic B quotes $5,800 but tells you they have “good insurance partnerships.” If your insurance plan actually covers part of diagnostic work or certain restorative categories, your out-of-pocket cost could be closer to Clinic A—or even lower for Clinic B—depending on eligibility. The only way to know is to understand plan rules and request itemized estimates that separate the components.
That is where consumer-facing insurance guidance (like the kind you’d expect to find on www.dentalplans.com) becomes useful: it helps transform “insurance is confusing” into a structured checklist for verifying what can reduce cost. Instead of guessing, you evaluate coverage categories, timing constraints, and documentation requirements.
Below is a compact comparison of websites that discuss low-cost dental implant options. The goal is informational transparency: readers can use these sources to understand common variables (process, pricing factors, implant types, and decision checkpoints). Note that website content is informational and not a substitute for clinical advice; the value is in understanding the decision factors you should ask about.
| Website | Common focus |
|---|---|
| Dental Views | Low-cost implant overview, treatment steps, and cost-related explanations |
| Atlantic Dental Group | Clinic services and scheduling pathway for a broad range of dental care |
| DentaVacation | Dental tourism approach, cost comparisons, and cross-border planning concepts |
| ADHP / plan-oriented guidance | Insurance plan concept for consumers and coverage-aware cost reduction |
Sources of the comparison information (links):
source: www.dentalviews.com
source: www.atlanticdentalgrp.com
source: www.dentavacation.com
source: www.rockvilledentalarts.com (Spanish page)
How to use these sources effectively:
In other words, the websites can help you structure your research. The clinical team you choose should help you validate which approach is safe for your specific anatomy.
In English-speaking markets, affordability discussions often emphasize documentation (treatment plans, itemized estimates, and follow-up protocols) as well as standardized clinic processes. Readers frequently compare:
For practical decision-making, many patients also look for insurance alignment: some plans are oriented toward preventive and restorative categories, and implant coverage can depend on policy language. Websites that explain implant options and planning logic can help readers ask better questions before committing to treatment.
Because “low-cost” offers can be complex, it helps to compare clinics through a shared framework. A structured framework reduces the risk of being misled by marketing. For example, if one clinic offers a lower “headline” price but charges separately for imaging, abutments, and lab work, the total treatment cost may not be comparable.
In English-speaking settings, you may also encounter common administrative steps that affect cost and timeline:
These administrative factors can be as important as the clinical plan itself. For example, a clinic might quote a “low-cost” implant pathway, but your insurance might require waiting until a certain time period is reached before a related service is eligible for coverage. If you plan around those rules, you can reduce out-of-pocket costs without compromising clinical standards.
In Spanish-speaking communities, it is common to value clear communication and accessible clinic information. Websites such as Rockville Dental Arts (Spanish version) are structured to serve Spanish-speaking patients with guidance that spans core dental services, including implant-related care. The broader benefit is not only translation—it’s the presence of a patient pathway: appointment scheduling, explanations of services, and a clinic ecosystem that can reduce friction during treatment.
When patients can understand the steps in their care plan, they are more likely to follow through with maintenance, show up for staged visits, and report complications early. That can indirectly influence both outcomes and costs by preventing avoidable complications.
In addition, some implant-focused clinics emphasize specific techniques. For example, Union City Mini Dental Implants concentrates on mini implants, which can be considered in select clinical scenarios where treatment design matches anatomy and functional goals. From an expert standpoint, the key is that mini implants are not universally appropriate; suitability depends on bone quality, occlusion, and the intended restorative plan.
If you’re comparing “low-cost” approaches in Spanish-speaking contexts, you’ll often want to clarify:
For insurance-aware decision-making, global health insurance providers such as Cigna provide educational implant guides that help patients understand the components of implant therapy and the factors that influence outcomes. When patients understand terminology (fixtures, abutments, prosthetic stages), they can better interpret quotes and coverage documents.
Another practical factor in Spanish-speaking regions is the impact of scheduling and language continuity. If you must switch providers mid-treatment due to translation barriers or administrative mismatch, that can create delays. Those delays can sometimes lead to increased costs through additional visits or extended timelines.
In Portuguese-speaking markets, affordability is often evaluated through combinations of clinic networks, service scope (from orthodontics to aesthetic dentistry), and plan-based approaches. For example, Rubi Odonto is described as offering services including implants, while Odontologia Velasco emphasizes up-to-date technologies and a broader portfolio including implants and prosthetics. On the plan side, DentalVidas is presented as a provider offering dental plans with a network of dentists and emergency availability.
From an industry expert perspective, patients should treat clinic portfolio and plan availability as variables to compare—useful, but not substitute for clinical evaluation. The “low-cost” strategy should begin with a diagnostic work-up, not with a price-first decision. If the clinic you choose can do diagnostics, surgery, and prosthetic work—or at least coordinate them effectively—this can reduce the risk of miscommunication across stages.
In many Portuguese-speaking contexts, there may be emphasis on having a single clinic “journey” for multiple dental needs. That can be beneficial when:
However, your main goal remains the same: confirm the clinical appropriateness of the implant plan and ensure the quote includes the steps necessary for safe completion.
For cost control, consider asking whether the clinic offers:
Again, low-cost is not only about the lowest price. It’s about predictable total spending and fewer avoidable complications.
The following ranges are provided as reference points for individual dental implants in the specified languages/country set. Actual pricing can differ due to implant type, number of implants, surgical complexity, and prosthetic design. Also note: “individual implant” pricing may still not include the full restorative package (crown, abutment, lab fees), depending on how a clinic structures its quote.
| Country | Currency | Price range (individual implant) |
|---|---|---|
| United States | USD | $3,000 - $6,000 |
| United Kingdom | GBP | £2,000 - £2,500 |
| Australia | AUD | AU$3,500 - AU$6,500 |
| Canada | CAD | CA$3,000 - CA$5,500 |
| Spain | EUR | €1,500 - €2,500 |
| Chile | CLP | CLP$800,000 - CLP$1,500,000 |
| Mexico | MXN | $15,000 - $25,000 |
| Colombia | COP | $2,000,000 - $4,000,000 |
| Peru | PEN | S/ 3,000 - S/ 6,000 |
| Argentina | ARS | $80,000 - $150,000 |
| Brazil | BRL | R$3,000 - R$8,000 |
| Portugal | EUR | €1,000 - €2,000 |
To use these numbers wisely, remember two key realities:
If you’re building a budget, it’s useful to ask clinics for a full breakdown: what portion is fixture/surgery, what portion is abutment and crown/bridge lab work, and what portion is imaging, post-op care, and maintenance.
Additionally, you should consider that “mini implants” and “full-sized implants” may be priced differently in some markets. Even if a mini implant is less expensive, the total prosthetic design might differ and could offset some of the savings. That’s why you must compare the entire treatment plan, not only the implant components.
This section explains a repeatable workflow for minimizing cost while maintaining quality signals. While the process is broadly applicable across regions, cultural expectations can vary—for instance, Spanish-speaking patients may prioritize Spanish-language communication and clear written explanations, while Portuguese-speaking patients may look for plan networks and service continuity. English-speaking patients often prioritize itemized documentation and standardized administrative steps (pre-authorization, annual maximum planning).
Regardless of language context, you can use the same core checklist: diagnostics first, itemized pricing second, coverage alignment third, and follow-up planning throughout.
Before you compare prices, request an evaluation that clarifies:
Why it lowers cost: Prevents paying for a “simple” implant plan that later changes due to anatomy. In clinical practice, unexpected grafting or staging is a common reason quotes rise. Diagnostic clarity protects you from “scope creep,” where the treatment becomes more expensive because your quote didn’t include necessary steps.
What to ask for during the diagnostic step: Request a written summary that includes the diagnosis, risk considerations (like periodontal stability), and the recommended treatment plan. If possible, ask the clinic to explain how their plan affects long-term durability (e.g., how they intend to manage occlusion forces and maintain gum health).
In Spanish-speaking and Portuguese-speaking contexts, you can reduce friction by requesting documentation in your language. If the clinic doesn’t provide written explanations, ask whether they can provide a translated summary or schedule a follow-up appointment with a translator.
When you compare clinics, ask for itemized estimates for each stage, such as:
In practice, itemized estimates make it easier to see what you are paying for and whether two quotes are comparable. If one clinic includes imaging and lab work in the total while another clinic lists only the implant fixture, you should not compare headline totals.
Tip for avoiding marketing confusion: Ask each clinic to confirm whether their quote includes:
If you can’t get itemized pricing, treat that as a sign to slow down. A lower price without itemization often hides extra cost later.
Low-cost implants are often achieved by reducing the amount you pay out of pocket for eligible services, even if implants are partially excluded. For readers considering dental insurance evaluation, www.dentalplans.com is relevant as a starting point for understanding coverage concepts and consumer decision criteria.
Practical insurance questions to ask:
To make insurance helpful for cost planning, you also need to coordinate timing. For example:
How to request coverage verification: Ask the clinic or your insurer for an estimate of benefits before you begin. In some situations, clinics can submit pre-treatment estimates that clarify what portion you might receive reimbursement for. You can then calculate your true cost: total treatment plan price minus estimated covered amount.
Insurance is not guaranteed to lower implant costs dramatically, but it can meaningfully reduce parts of the journey. Many patients find that even if implants are excluded, the plan may cover exams, some diagnostic imaging, or certain restorative components.
Depending on your situation, “low-cost” might come from:
It’s helpful to distinguish between “low-cost” that reduces medical steps and “low-cost” that reduces administrative overhead or allows payment spread. Both can help, but only one should be used for clinical simplification—and that should never happen without diagnostic justification.
Clinic bundles: Bundles can be a strong value if they include everything needed for completion. However, you should read the fine print. Some bundles include diagnostics but exclude crown fabrication; others include the surgical stage but not long-term maintenance. Always request a written scope of what is included.
Financing plans: Financing can improve affordability even when the clinical plan is not cheaper. But you should ask:
Alternative implant designs: Mini implants may be less expensive in certain markets, but they’re not a universal solution. Clinical appropriateness matters. If the clinic is proposing mini implants, ask why they’re suitable for your bone and functional requirements. Also ask how they plan to handle the bite forces and long-term maintenance.
Technology and process efficiency: Sometimes “low-cost” clinics use more efficient workflows or have strong lab partnerships that reduce turnaround time. That can reduce operational overhead. But technology itself shouldn’t be the selling point; outcomes and appropriate indications should be.
Some patients reduce costs by traveling for treatment. A dental tourism approach (as discussed by resources like DentaVacation) can lower surgical and prosthetic expenses in certain destinations. However, from an expert standpoint, the “hidden cost” is often post-treatment care: complications, adjustments, and good maintenance.
If traveling, you should plan for follow-up as though you might need additional visits. That means you should ask for documentation you can share with a local provider if necessary.
Checklist for safe dental tourism planning:
Why follow-up matters clinically: Even uncomplicated implant cases often require adjustments and monitoring. Prosthetics may need bite refinement. Soft tissue health needs evaluation. If you return home without continuity of care, problems can linger and become more expensive.
Some patients assume warranty will cover them automatically. But warranty coverage can vary by what caused a complication and whether it’s considered a “return visit” vs. requiring local care. Always request the warranty terms in writing and clarify what is included.
Dental tourism can still be a valid cost strategy for some people, but it must be treated as a coordinated medical plan rather than a vacation purchase. The cheaper price is only truly “cheap” if you can maintain the implant long-term.
Once you have itemized costs, discuss options such as:
Negotiation works best when you have clarity. If you can identify what is included, you can ask targeted questions. For instance, if Clinic A’s price includes both imaging and follow-ups while Clinic B’s doesn’t, you can negotiate by requesting an “apples-to-apples package.”
However, there are limits. You should not negotiate away medically necessary steps. If bone grafting is indicated, delaying or skipping it can jeopardize outcomes. Instead of focusing only on price reductions, focus on removing unnecessary extras and aligning the plan with what your diagnostics actually support.
In family contexts, negotiation also includes planning around time. Sometimes you can save indirectly by reducing the number of visits required for specific steps—if the clinic offers coordinated scheduling that prevents repeating scans or consultations.
Affordable implants are not only about surgical placement; they also depend on:
Maintenance costs should be included in your budget. Many people focus on the implant fixture cost and forget that long-term success often requires ongoing dental visits. If the clinic includes maintenance for a certain period in its warranty, that may reduce risk. If it does not, you should plan for these follow-ups separately.
Also consider that prosthetics may need repairs or replacements over time. Different materials and design choices can affect longevity and repair frequency. If a low-cost plan uses lower-cost prosthetic materials, it might still be appropriate, but you should ask about expected lifespan and maintenance requirements.
Finally, implant success is not only clinical—it’s behavioral too. If you anticipate difficulty keeping up with hygiene or regular visits, discuss that during consultations. A good clinic will help you tailor the plan realistically to your circumstances.
Language-specific note on communication support:
In all cases, effective communication reduces mistakes—such as missed appointments, unclear aftercare instructions, or misunderstanding warranty procedures.
From a clinical governance standpoint, affordability programs still require medical suitability. Common requirements or constraints include:
Low-cost pathways often have eligibility criteria. Sometimes the “low-cost” is available only for certain implant sites, certain case complexity levels, or certain restorative designs. If a clinic markets “low-cost implants” broadly, it is still important to confirm whether your case meets the criteria.
Why eligibility matters for cost: If you qualify, the low-cost plan might be appropriate and complete. If you do not qualify, you may need extra steps (grafting, additional stabilization, periodontal therapy), which can erase the savings. Therefore, diagnostic evaluation is not optional; it is the foundation of cost control.
Below are additional factors that can influence cost and timing and should be discussed early:
Even if your goal is low cost, the safe path is typically: stabilize health first, then place implants in a way that supports long-term success.
No. A low-cost offer may reflect transparent bundling, different market pricing, or selected treatment design. However, quality concerns typically arise when a quote is incomplete (not itemized), when implant system details are unclear, or when the clinic cannot explain diagnostic findings and staging requirements. Always request an itemized plan and ask about materials, follow-up, and warranty.
To differentiate “lower quality risk” from “lower price due to efficiency,” you can ask for specifics: implant brand and model, abutment type, crown material, expected timeline, and included follow-up. When these are clear, low-cost can sometimes be a real value.
Coverage varies widely by plan rules, eligibility, waiting periods, and policy language. Some plans cover related diagnostic services, preventive care, or portions of restorative work, while implant-specific coverage may be limited. Using an insurance planning approach—such as the consumer-oriented evaluation associated with www.dentalplans.com—can help you estimate out-of-pocket costs more accurately.
Insurance coverage also varies by how services are coded and documented. If your clinic provides careful documentation and itemization, you may have a better chance of coverage for eligible categories. This is not “gaming the system”; it’s ensuring the paperwork matches what you actually need clinically.
Total cost often includes diagnostic imaging, surgical placement, implant fixture and abutment, the final crown/bridge/denture, laboratory/prosthetic work, and follow-up visits. A quote that only references the implant fixture is usually insufficient for realistic budgeting.
Also consider indirect costs that matter to families: transportation, time off work, child care or elder care needs, and possible financing fees. Some people can tolerate out-of-pocket costs but cannot tolerate long delays. Your budget should consider both direct and practical costs.
Sometimes staged treatment can reduce short-term payment burden through phased scheduling, but staging does not automatically reduce overall clinical cost. The right approach depends on your anatomy, infection risk, healing time, and prosthetic timeline.
There’s a tradeoff: staged treatment may spread costs over time, making affordability easier. But longer timelines might increase the number of visits and potentially maintenance costs. The best choice depends on your clinical needs and your financial structure.
Mini implants may be lower cost in certain scenarios, but they are not universally appropriate. Clinical suitability depends on bone conditions, functional load, and the restorative plan. Patients should avoid assuming mini implants are always the low price option.
Mini implants can be appropriate in specific cases, but the correct comparison is the entire restorative outcome: stability, bite function, hygiene access, and expected longevity. Sometimes a slightly higher implant fixture cost can produce a more durable and maintainable prosthetic solution.
Request the same category of information from each clinic: imaging evidence, implant system details, itemized pricing, warranty terms, and the follow-up schedule. Compare using identical assumptions about the number of implants and prosthetic design.
Also be cautious about “too good to be true” promises. Low-cost clinics should still be transparent. Ask for how complications are handled, what happens if bone grafting becomes necessary, and whether the quoted price includes necessary extractions or periodontal stabilization.
Key risks include delayed complications, limited continuity of care, mismatched warranty terms, and difficulty coordinating good maintenance after returning home. If traveling, treat follow-up and documentation as non-negotiable requirements.
One practical step: request copies of all imaging and documentation (CBCT reports, implant system details, operative notes, prosthetic material specs). If you need local care later, these documents can help your follow-up provider understand what was done and reduce delays.
Ask what is covered if complications arise, what is considered normal adjustment vs. repair, and what follow-up is required. Also ask about maintenance expectations (e.g., routine checkups and hygiene). Implant success is typically linked to good oral health management.
Be specific: if a crown chips or needs replacement, is that covered? If a complication is due to peri-implantitis, does warranty cover treatment or only the implant itself? Clear language matters because outcomes and responsibilities can be disputed without documented terms.
From an industry expert’s view, the top affordability strategy is evidence-based and transparent. “Low-cost” is not a marketing slogan—it’s a structured decision process that reduces unnecessary spending while protecting outcomes.
The key takeaways include:
Another expert perspective: many “low-cost” decisions fail not because the implant itself is wrong, but because the plan wasn’t complete. A partial plan that omits imaging, abutments, lab fees, or follow-up care can be cheaper on paper and more expensive in total once the case requires additional appointments.
Therefore, insist on full scope clarity:
When those questions are answered clearly, “low-cost” becomes a legitimate strategy rather than a gamble.
Finally, remember that outcomes are influenced by clinician skill and patient compliance. You don’t need to choose the most expensive clinic, but you should choose the clinic that can demonstrate competence, transparency, and a realistic plan for your specific case. Your “value” comes from the intersection of appropriate clinical indication, clear pricing, and reliable long-term support.
Dental implants can be life-changing, but affordability planning must be structured. “Low-cost” should be treated as a decision framework—diagnostic clarity, itemized comparisons, and coverage-aware budgeting—rather than a single number.
In English-, Spanish-, and Portuguese-speaking countries, patient needs may vary (communication preferences, plan networks, and follow-up expectations). Yet the safest cost-control approach remains the same: ask for documentation, verify clinical fit, and evaluate total treatment journey costs. Whether you use insurance resources like www.dentalplans.com to understand coverage concepts or you compare clinics using itemized estimates, your goal should always be clarity and continuity.
When “low-cost” decisions are evidence-based and follow-up is planned, you’re more likely to achieve both financial control and a successful long-term implant outcome.
1) The above information comes from online resources, and the data is as of October 2023. 2) Dental implant prices are for reference only and may vary by region, clinic and doctor.
Reference links (all links used in this article):
https://dentalviews.com/low-cost-dental-implants/
https://www.atlanticdentalgrp.com/
https://www.dentavacation.com/
https://rockvilledentalarts.com/es/
https://www.dentalplans.com
Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans

Explore the Tranquil Bliss of Idyllic Rural Retreats

How to Make Lasting Memories at Disneyland Attractions

4rkojvsx Technology: Industry Insights and Buying Guide

Affordable Phones and Plans for Seniors

Affordable Full Mouth Dental Implants Near You
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!

Discovering Springdale Estates

Unveiling RS Sul Telecom Services

Affordable Full Mouth Dental Implants Near You
Discover options for affordable full mouth dental implants, including clinical trials and local dental services that offer cost-effective solutions.

Understanding Full Mouth Dental Implant Prices
Explore the costs and factors influencing full mouth dental implants for seniors and others.
Comprehensive Guide to Dental Implants
This comprehensive guide delves into the intricacies of dental implants, providing a global perspective with a special focus on Implantswiss. Dental implants, a pivotal advancement in restorative dentistry, offer solutions for missing teeth, aiding in oral health and functionality. This article navigates through cost-effective solutions, global pricing comparisons, and the role of Implantswiss in elevating dental care standards internationally.

Affordable Dental Implants Near You
Discover low-cost dental implants and quick solutions to fix your teeth with full mouth options available near you.

Understanding Dental Implant Prices and Options
Explore dental implant costs, funding, and full mouth options for a confident smile in 2025.

Affordable Dental Implants Near Me: Your Guide
Discover affordable dental implants, funding options, and fast solutions for fixing your teeth near you in 2025.
