This guide explains how PeopleSoft HHC supports healthcare information management across core administrative workflows. Objectively, “PeopleSoft” is an established enterprise platform, while “HHC” is commonly used to denote healthcare-related operations in many organizations. The article clarifies typical modules, governance considerations, integration patterns, and practical decision criteria for implementation.

PeopleSoft HHC is commonly referenced when healthcare organizations look to standardize administrative and information workflows on an enterprise platform. In practice, organizations use PeopleSoft tools to coordinate day-to-day processes such as eligibility and operations tracking, finance workflows, HR administration, reporting, and document-driven coordination. When “HHC” is used in an organizational context, it often signals a healthcare-focused deployment scope—meaning the PeopleSoft implementation is tailored to the operational realities of healthcare delivery, compliance expectations, and multi-department reporting.
Because healthcare is operationally complex and documentation-heavy, the very valuable outcomes from a PeopleSoft HHC approach typically come from governance, audit readiness, data consistency, and repeatable workflows—not from a single feature alone. A credible implementation therefore emphasizes process design, role-based access, integration hygiene, and decision-support reporting, so the organization can reduce manual reconciliation and improve visibility across programs.
In many health systems and public-facing health organizations, administrative work is where risk accumulates: incorrect funding codes can distort financial reporting; inconsistent cost centers can produce misleading dashboards; and weak access controls can lead to inappropriate edits to sensitive records. PeopleSoft HHC is therefore less about “software adoption” and more about instituting an administrative operating model that supports governance, defensible reporting, and operational continuity through change.
To make this tangible, consider the difference between a spreadsheet-driven environment and a governed enterprise system. In a spreadsheet approach, the organization often relies on people’s memory, informal conventions, and repeated manual steps. In PeopleSoft HHC, the organization instead defines “rules of record” for coding, approval chains, audit logs, and reporting hierarchies. That difference is what enables auditability and helps leaders act on reliable information rather than on approximations.
Furthermore, healthcare organizations frequently operate across multiple legal entities, service locations, programs, grants, and funding sources. Administrative data must therefore be modeled so that the organization can reconcile across dimensions: the same employee may be part of multiple reporting lines over time; the same program may have different accounting structures depending on funding source; and the same operational event (e.g., staff reclassification) can have downstream impacts on payroll, budgeting, and reporting extracts. A PeopleSoft HHC approach—done responsibly—supports those complexities through structured configuration and traceable workflows.
“PeopleSoft” generally refers to a long-running enterprise application ecosystem used by universities, governments, and large enterprises for HR, finance, and operational reporting. In many healthcare-related deployments, teams adapt configuration and processes to align with healthcare administrative needs.
“HHC” very often appears as an abbreviation that an organization uses to denote a healthcare-related scope—such as a health authority, a hospital and care program, a community health initiative, a healthcare services division, or a healthcare-focused business transformation program. The term is not standardized globally in a single universal way, so the safest professional assumption is that “HHC” in any given project is an internal shorthand for the healthcare operational domain and associated reporting priorities.
For decision-makers, the key objective understanding is this: PeopleSoft provides the structural platform; the healthcare “HHC” meaning defines the workflow and reporting environment you must design around—such as patient-facing program coordination (where applicable), staff scheduling/HR processes, finance and grants accounting, and compliance-oriented reporting.
It’s also important to recognize that “HHC” may reflect organizational boundaries rather than system boundaries. For example, a health authority may use PeopleSoft to coordinate multiple hospitals or community programs. In that scenario, “HHC” is effectively the enterprise scope of the healthcare business domain. The PeopleSoft configuration and governance decisions—data ownership, security policies, chart of accounts hierarchies, and integration rules—become the mechanisms that align multiple parts of the organization under a common administrative standard.
Because the abbreviation is not globally standardized, the most effective way to avoid confusion is to confirm the meaning of “HHC” during discovery. Stakeholders should document: (1) what departments are included, (2) what processes are in scope, (3) what reporting outputs are required, and (4) what constraints apply (e.g., audit requirements, funding program rules, or data privacy expectations). This single clarification often prevents the kind of scope drift that can otherwise derail a PeopleSoft HHC initiative.
From an industry expert perspective, healthcare organizations usually adopt enterprise systems in layers. PeopleSoft HHC very commonly supports the “back office that makes operations run” and the “administrative backbone that enables service delivery.” Even when clinicians primarily use separate clinical systems, PeopleSoft-style administration often connects to staffing, costing, budgeting, procurement/finance, and consolidated performance reporting.
Many leaders initially think of PeopleSoft in terms of classic HR and finance. In healthcare transformations, however, PeopleSoft is often extended to cover operational administration such as eligibility verification workflows (where applicable), program operations tracking, document lifecycle controls, and structured reporting that links administrative activity to operational outcomes.
1) HR and workforce administration. Healthcare environments rely on workforce planning, credentialing-related processes (depending on configuration), staffing structures, and payroll/benefits alignment. PeopleSoft-style HR administration can become the authoritative reference for organizational structure and employee records. This becomes critical when the organization operates across multiple unions, pay types, or employment categories. A well-governed PeopleSoft HHC environment supports consistent job/position structures, reliable assignment histories, and repeatable processes for approvals and adjustments.
In addition, healthcare workforce data often changes due to reclassifications, transfers, leave events, and temporary assignments. These changes must be reflected in downstream reporting so that leaders can accurately assess capacity and budget utilization. PeopleSoft HHC implementations commonly treat HR as a foundational data domain—meaning other modules and integrations rely on the HR data being correct and timely.
2) Finance and compliance reporting. Healthcare operations often involve restricted funds, program-based accounting, and multi-entity reporting. PeopleSoft HHC implementations usually focus on creating consistent chart-of-accounts structures, approvals, audit trails, and period-end controls aligned to organizational policies.
Healthcare finance reporting can be particularly sensitive because it may feed statutory reporting, grant reporting, or compliance reporting to regulators and funding bodies. PeopleSoft HHC initiatives often therefore include strong control design: approvals for journal entries, permissions for posting and adjusting, and traceability for how transactions flow from operational events to financial reporting outputs.
3) Reporting and operational analytics. Leaders require operational reporting that ties administrative activity to program outcomes, staffing availability, and budget utilization. PeopleSoft environments often provide reporting frameworks that can be complemented by separate data warehouses or BI tools.
In successful programs, reporting is not treated as an afterthought. Instead, the organization defines key performance metrics early and ensures that PeopleSoft data structures support those metrics. For example, cost center hierarchy and funding program coding must align to the reporting dimensions required by leadership dashboards. Similarly, workforce reporting often needs time-based and organizational rollup structures, so the system’s assignment and history structures must be designed accordingly.
4) Integration with other healthcare systems. PeopleSoft HHC frequently needs careful integration with external systems such as identity management, document storage, data warehouses, or other operational applications. The “top” PeopleSoft outcome usually appears when integration is treated as a governance discipline rather than an afterthought.
Healthcare organizations also face challenges such as data latency, multiple source systems for “truth,” and the need to protect sensitive information. PeopleSoft HHC integration design therefore often includes: validation rules; error-handling and retry strategies; monitoring dashboards; and a clear contract of ownership for each data element (including who is responsible for corrections if data conflicts are detected).
When integration governance is weak, reporting can become unreliable. For example, if the identity system provides incorrect role assignments, PeopleSoft security can fail; if the HR system sends incorrect cost center codes, finance reports may show transactions in the wrong dimension; and if document flows are not controlled, audit evidence may be missing. Treating integration hygiene as a core PeopleSoft HHC practice helps prevent these failure modes.
Many projects fail not because the platform is incapable, but because implementation governance is weak. Professionals typically judge success by how reliably the system supports repeatable workflows, maintains data integrity, and enables traceable decision-making.
In healthcare, traceability is more than convenience. It is often required to answer questions such as: Who approved a change? When did it happen? What underlying event triggered it? What version of the configuration or logic was applied? And what evidence exists to support the transaction? A strong PeopleSoft HHC implementation is therefore built to support not only operations, but also investigation and audit.
Beyond the bullet points above, professionals often add one more distinguishing characteristic: thoughtful data modeling. PeopleSoft HHC success often depends on how well the organization models its reporting dimensions and histories. Healthcare administrators frequently need “as of” views: what was true on a specific date. To support that, the data model must correctly represent effective dates, assignment histories, and dimension rollups over time.
You asked to incorporate price information and supplier details; however, no specific price, supplier name, city, country, or official pricing figures were provided in the input. In professional practice, PeopleSoft HHC project costs vary widely based on scope, existing landscape, integration complexity, number of modules, environment requirements (dev/test/prod), reporting needs, and implementation services.
Accordingly, the very objective way to evaluate “price” is to treat it as a range determined during discovery. Very buyers should expect cost drivers such as licensing/maintenance arrangements (as applicable), implementation services, integration work, data migration, testing effort, training, and ongoing operational support.
However, mature procurement practices in healthcare go beyond looking at total cost. They also evaluate whether the supplier’s delivery approach reduces risk and rework. A slightly higher initial cost may be worthwhile if the vendor delivers stronger governance artifacts, better test coverage, robust integration monitoring, and a support model designed for healthcare operational continuity.
When comparing suppliers for PeopleSoft HHC, decision-makers also commonly assess:
Below are common scope areas that discovery teams consider when defining a PeopleSoft HHC deployment. The emphasis is on what teams need to document and govern, rather than on feature checklists. Discovery should output concrete artifacts such as scope boundaries, data ownership maps, integration inventories, and acceptance criteria for critical reporting outputs.
To make discovery more actionable, teams frequently produce a “scope map” showing what belongs to PeopleSoft HHC versus what will remain in other systems. This map reduces the risk that stakeholders assume PeopleSoft will solve all challenges, when in reality PeopleSoft is an administrative backbone that integrates with the broader healthcare ecosystem.
The table below serves as a comparison of common decision dimensions teams consider for PeopleSoft HHC initiatives. It is written to help stakeholders evaluate options objectively and avoid scope ambiguity.
| Decision dimension | What to clarify for PeopleSoft HHC | Why it matters in healthcare administration |
|---|---|---|
| Scope boundaries | Which departments and workflows are included (HR, finance, reporting, program administration), and what is explicitly out of scope | Prevents under-delivery and reduces rework during rollout |
| Data governance | Definitive data owners for key domains (employee, cost center, funding codes, organizational hierarchy) | Improves reporting consistency and audit traceability |
| Integration strategy | Systems involved, direction of data flow, validation rules, and monitoring approach | Reduces broken reporting and downstream operational friction |
| Security and controls | Role design, approval chains, and audit logging expectations | Supports compliance and minimizes the risk of unauthorized changes |
| Testing rigor | Test scenarios, data quality checks, and acceptance criteria for critical reports | Maintains confidence in financial and operational reporting outputs |
| Operational readiness | Support model, release management, and incident workflows | Ensures sustainability after go-live |
In practice, stakeholders often use the dimensions above to create a “requirement confidence score.” For example, if scope boundaries are unclear and integration monitoring is not defined, the overall risk is higher even if the platform is proven. This helps governance teams prioritize discovery work and reduce late-stage surprises.
In enterprise and regulated environments, practitioners generally anchor implementation practices in established guidance from standards bodies, industry frameworks, and vendor documentation. For security and governance practices, teams often align to widely used security controls and auditing principles. For implementation and reporting reliability, teams rely on recognized software testing methodologies and data governance approaches.
Note: Specific claims about “price,” “supplier,” or localized implementations should be verified using your procurement documents and vendor statements, as the provided input did not include such factual details. For reference, organizations commonly consult:
Additionally, healthcare organizations frequently consult internal policies and external regulatory expectations that govern auditability, access control, and data handling. Even when PeopleSoft HHC is deployed as an internal administrative platform, it often touches data governed by privacy regulations, funding rules, and retention requirements. Therefore, top practice evidence is often a combination of vendor guidance, external security frameworks, and internal governance documentation.
This step-by-step guide is designed to help stakeholders structure PeopleSoft HHC work in an objective and auditable manner. It focuses on governance and delivery practices rather than marketing promises. In healthcare, where operational continuity matters, the “responsible implementation” approach also includes building a realistic plan for operational support and training.
Step 1: Establish the governance team. Assign owners across HR, finance, reporting/BI, security, integration, and operational support. In healthcare contexts, you also want stakeholders who understand compliance workflows and operational cadence. Ideally, governance roles include: a business process owner (who signs off on workflow behavior), a data stewardship lead (who owns data definitions and hierarchies), and a control/audit liaison (who ensures evidence expectations are included).
Step 2: Perform a requirements discovery workshop. Map current administrative processes end-to-end. Identify pain points such as manual reconciliation, inconsistent coding, unclear approval chains, and reporting gaps. Capture system touchpoints and data sources that will feed reporting outputs.
To increase quality, discovery workshops should capture not only process steps but also decision rules and exception handling. For example, if a cost center changes mid-period, what is the expected financial treatment? If an employee’s reporting line changes due to organizational restructuring, how are historical reports expected to behave? These “process nuance” questions often determine whether the PeopleSoft HHC implementation will meet operational expectations.
Step 3: Define the data dictionary and hierarchy rules. Decide how key entities will be represented. This includes organizational hierarchies, employee identifiers, cost center structures, funding/program codes, and reporting dimensions. Document the “rules of record” so stakeholders do not rely on tribal knowledge.
A data dictionary should be more than a list of fields. It should define: ownership; validation rules; effective dating rules; allowable values; and how changes are handled over time. In healthcare finance and HR, these definitions are critical because they determine how “as-of” reporting works and how audit investigators interpret historical transactions.
Step 4: Build the security and audit model early. Create role templates aligned to separation-of-duties expectations. Specify who can view, approve, modify, and export administrative reports. Ensure audit logging requirements are understood before configuration begins.
Security design should include both functional and technical considerations. Functional considerations include who needs what permissions for each workflow stage. Technical considerations include how audit logs are retained, how access changes are tracked, and how exports are controlled. In many healthcare environments, data exports must be controlled or logged, especially when outputs contain sensitive administrative information that could be relevant to compliance investigations.
Step 5: Create an integration blueprint. Inventory upstream and downstream systems. Define data mapping, validation rules, error handling, and monitoring. Establish whether changes require versioning or contract updates so reporting remains stable.
Integration governance also includes decisions about event timing. For example, if HR changes are made during a payroll cutover period, when should the finance reporting dimension update? If identities are synchronized nightly, what happens when a new user is created mid-day? These operational timing questions determine whether PeopleSoft HHC will feel reliable to end users.
Step 6: Configure workflows and approval chains. Implement business rules based on documented processes. For approvals, define the correct chain of responsibility and how exception handling works. Ensure that workflow outcomes are traceable.
This step is often where implementations succeed or fail. Healthcare administrative workflows frequently involve multiple stakeholders and require predictable outcomes. If approval logic is unclear, users may bypass the workflow, delay actions, or escalate repeatedly. A strong PeopleSoft HHC implementation defines workflow steps, validations, and exception routing so that every administrative transaction has a clear lifecycle and evidence trail.
Step 7: Migrate data with validation gates. Data migration should include cleansing, deduplication logic (as appropriate), and validation checks. Define acceptance criteria for key entities (e.g., employee records and finance dimensions).
Data migration planning should include both technical and business validation. Technical validation checks include mapping completeness, referential integrity, and field-level formatting. Business validation checks include verifying that hierarchies and codes match expected reporting structures. For example, if funding program codes differ slightly between legacy systems and PeopleSoft HHC, reconciliation may become impossible without clear mapping and documentation.
Step 8: Test with scenario coverage that reflects healthcare realities. Testing should include edge cases such as corrections, reclassifications, back-dated adjustments, and report reconciliation scenarios. Confirm that critical reports tie to underlying transactions.
A comprehensive PeopleSoft HHC testing approach often includes: functional testing for each workflow; integration testing for data exchange reliability; security testing for access controls; and performance testing if reporting loads are significant. For healthcare, testing also often includes “operational readiness testing,” such as verifying the ability to handle unusual request patterns, role changes, and high-volume reconciliation periods.
Step 9: Train users with role-based learning paths. Healthcare administrative users often have distinct responsibilities. Training should reflect daily tasks, approval responsibilities, and “what to do when something is off.”
Good training also includes guidance on how to interpret errors and rejections, how to correct transactions through PeopleSoft workflows, and how to escalate issues to support teams. Because administrative environments rely on human judgment and timely response, training often becomes a risk reduction lever. Teams can reduce post-go-live issues by ensuring users understand not only “how to click,” but also “why a validation exists,” and what the system expects at each step.
Step 10: Go-live with operational readiness and monitoring. Ensure incident response procedures, escalation paths, monitoring dashboards, and post-go-live support windows are ready. Validate report outputs immediately and establish a reconciliation cadence.
Operational readiness includes more than technical readiness. It also includes communication readiness—who is the point of contact for issues, how updates are communicated to stakeholders, and how urgent incidents are prioritized. In healthcare, where operational peaks occur, a strong go-live plan anticipates those peaks rather than assuming a stable environment after rollout.
Step 11: Governance after launch. Establish a change control process for configuration updates and report logic. Regular audits of access roles and data quality checks help keep the PeopleSoft HHC environment trustworthy over time.
Post-launch governance should include: periodic access review, data quality monitoring routines, and controlled release management. Many healthcare organizations also implement quarterly or semi-annual control reviews to confirm that separation of duties remains intact as teams reorganize and staffing changes. PeopleSoft HHC governance should adapt to organizational change while maintaining controls.
Below are commonly encountered conditions and requirements for PeopleSoft HHC initiatives. These are phrased as practical checklist items to help teams avoid avoidable delays.
In many healthcare transformations, the biggest hidden cost is not the platform or integration effort; it is the cost of ambiguity. When data ownership is unclear, teams spend time reconciling definitions. When security requirements are unclear, teams spend time reworking role models. When reporting acceptance criteria are unclear, stakeholders repeatedly reject outputs. Planning for these conditions in discovery and early governance reduces rework.
Your instructions included a localization rule to replace any occurrence of city/country placeholders with “nearby.” No city or country appears in the provided keywords, so no replacement was required. Still, localization in healthcare system programs often means aligning training examples, approval workflows, and reporting hierarchies to the organization’s operational footprint—whether that footprint is a single facility or multiple nearby service locations.
In practical PeopleSoft HHC terms, localization may also involve customizing role templates, operational approval chains, and reporting rollups to match how governance is structured locally. For example, a facility director may approve certain HR actions while a centralized governance team approves finance allocations. Localization should not be superficial; it should reflect how administrative authority is distributed in the organization.
Another localization consideration is language and user experience. While PeopleSoft implementations often focus on configuration, healthcare organizations also need to support consistent terminology. If stakeholders use different terms for the same concept (e.g., “program,” “service line,” “initiative”), then reporting may become inconsistent. A PeopleSoft HHC implementation should therefore define consistent labels and mapping between terms, and ensure training material uses the same vocabulary.
In practice, it refers to a PeopleSoft-based implementation tailored to a healthcare-focused administrative scope (“HHC” as an internal shorthand for the healthcare operations domain). The exact meaning of HHC depends on the organization’s terminology and should be confirmed during discovery.
For example, in one organization “HHC” may represent a hospital and care program unit that needs HR and finance administration. In another organization, “HHC” may represent a broader healthcare authority with multi-entity financial reporting and program-level funding compliance. The PeopleSoft platform remains the same class of enterprise tool, but the workflow and governance requirements are defined by the meaning of HHC in that organization.
Commonly, HR, finance, and reporting/operations stakeholders use the system for administrative workflows, approvals, accounting structures, and performance reporting. The scope varies based on how the healthcare organization defines the HHC domain.
Many programs also involve procurement, grant management, and operational administrators who maintain program documentation. While clinicians may not directly use PeopleSoft HHC day-to-day, they can still be impacted through staffing allocations, budgeting constraints, and operational reporting that influences service planning.
Usually, PeopleSoft-style environments do not replace clinical systems. They typically support administrative and enterprise reporting workflows that connect to clinical or operational data through controlled integrations.
In healthcare ecosystems, clinical systems are often specialized and optimized for patient care workflows, documentation, ordering, and clinical decision support. PeopleSoft HHC usually complements these systems by handling administrative and financial operations. The integration between clinical and administrative systems—when required—must be governed carefully to ensure data correctness and compliance.
Strong implementations use role-based access controls, separation of duties for approvals, and audit logging. Security requirements should be defined early, then validated during testing with representative administrative scenarios.
In healthcare, security also often needs to consider operational realities. For example, temporary staff or rotating managers need limited, time-bound access. PeopleSoft HHC can support this through role templates and controlled processes for granting and revoking access, but the organization must define clear operational procedures so that access changes happen reliably and are auditable.
Common risks include unclear scope, inconsistent data governance, under-specified integration validation, weak testing for reconciliation scenarios, and insufficient operational readiness after go-live.
Another risk is over-customization without clear governance. If teams customize too much without solid traceability, upgrades and future changes can become expensive. Responsible PeopleSoft HHC implementations balance configuration choices with maintainability, documenting what is configured, why it is configured, and what dependencies exist.
Teams typically validate report outputs against underlying transactions and define reconciliation procedures with acceptance criteria. Critical reports should include scenario testing and sign-off from process owners.
Validation should also include “dimension checks” where stakeholders confirm that rollups by cost center, funding program, and organizational hierarchy match expectations. Because healthcare reporting is often multi-dimensional, report accuracy depends as much on correct coding and governance as on the report layout itself.
Because pricing depends on scope and services, teams usually treat “price” as a procurement outcome derived during discovery: licensing/maintenance (as applicable), implementation labor, integration effort, testing and training, and ongoing support. Without your specific procurement inputs, any fixed number would be speculative.
In procurement practice, buyers also evaluate contract terms. For example, they may require performance and acceptance criteria in the contract, define how change requests are handled, and request clarity on who owns defects and remediation. These contract terms can materially affect total project cost by reducing rework.
Buyers should request supplier evidence of comparable implementations, delivery methodology, security and testing approach, integration governance plan, project timeline structure, and support model details. Where applicable, request references tied to healthcare administrative workflows.
It’s also useful to ask for sample governance artifacts: a sample security model approach, a data dictionary template, a test strategy outline, and an example of how the supplier handles reconciliation and report sign-off. These artifacts help buyers assess whether the supplier has repeatable methods aligned to governance and audit readiness.
Very healthcare organizations have compliance expectations around access control, auditability, and data handling. Exact requirements depend on jurisdiction and organizational policies, so teams should confirm regulatory and internal control obligations before configuration decisions are finalized.
Even when PeopleSoft HHC is primarily administrative, it can include sensitive information such as workforce details, organizational structures, and financial records. Compliance can therefore influence data retention, audit logging, and reporting access. A responsible program plans compliance early so that security and evidence requirements are built into the system rather than bolted on later.
Implementation timelines vary significantly depending on modules, integration complexity, data migration readiness, and testing coverage. A responsible approach is to build a plan with milestone-based validation gates rather than relying on generic duration estimates.
In healthcare, timeline risk also depends on operational availability for testing and sign-off. If business owners cannot dedicate time during critical windows, validation delays can extend timelines. A responsible plan anticipates this by scheduling business participation and governance checkpoints early.
PeopleSoft HHC is top understood as a healthcare-tailored administrative operating model built on an enterprise platform. The strongest results generally come from careful governance: well-defined data ownership, a security design that supports auditability, integration contracts that preserve reporting integrity, and testing that reflects real operational scenarios. When these foundations are in place, PeopleSoft HHC initiatives can deliver dependable administrative workflows and more reliable decision support for healthcare organizations.
To get lasting value, leaders should also invest in post-go-live maturity. That includes ongoing access reviews, data stewardship routines, integration monitoring, and change control procedures that ensure the system continues to reflect how the healthcare organization operates. Without those routines, even a well-implemented system can drift into inconsistent practices over time.
If you share your intended HHC scope (e.g., HR-only vs. HR + finance + reporting), your integration landscape, and any procurement constraints, I can help refine a more tailored PeopleSoft HHC blueprint—still keeping recommendations grounded and verifiable.
Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans

Explore the Tranquil Bliss of Idyllic Rural Retreats

How to Make Lasting Memories at Disneyland Attractions

4rkojvsx Technology: Industry Insights and Buying Guide

Affordable Phones and Plans for Seniors

Affordable Full Mouth Dental Implants Near You
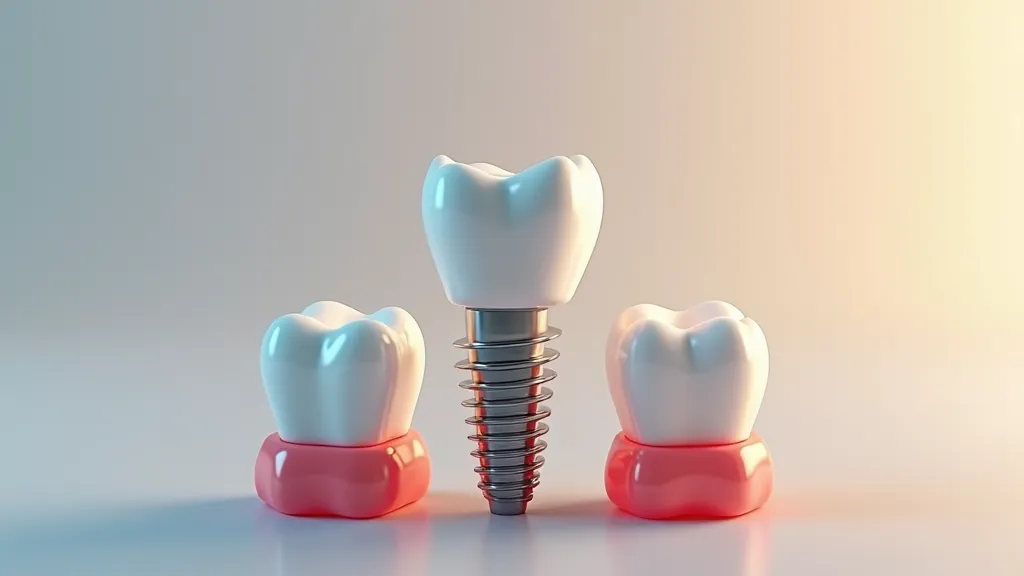
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!

Discovering Springdale Estates

Unveiling RS Sul Telecom Services

Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans
Finding an optimal mix of insurance premiums and direct medical costs is crucial for effective healthcare budgeting. This discussion will delve into tactics to achieve a balance that aligns with your finances.
4rkojvsx Technology: Industry Insights and Buying Guide
This guide explains 4rkojvsx with an evidence-based, step-by-step approach to evaluating suppliers, pricing, and requirements before purchasing. Objectively, the term points to a technical category where compatibility, quality controls, and documentation matter as much as the nominal price. Readers will also find a practical comparison table, conditions, and targeted FAQs.
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!
Selecting an adept dentist is critical for ensuring the efficacy and your satisfaction during a dental implant procedure. This in-depth guide is designed to assist you in finding a dental expert who meets your personal requirements, guaranteeing that your path to dental implant success is seamless and fruitful.
Protect Your Perfect Smile: Master the Art of Defending Your Teeth Against Acid Attacks
Though they may tantalize the palate and invigorate the senses, foods and drinks with high acid content are a double-edged sword with regard to oral wellness. Continual exposure to these substances progressively strips away the protective enamel from our teeth, which can lead to increased sensitivity, changes in coloration, and a variety of other dental complications. This composition offers insight into relishing these zesty favorites while safeguarding your teeth from damage.

Comprehensive Insight into Boob Enhancement
Boob enhancement is a cosmetic procedure aimed at augmenting the size and improving the shape of breasts for aesthetic purposes. With the evolution of medical procedures, this enhancement has become more sophisticated, offering various options to cater to individual preferences and needs. This detailed guide explores the intricacies of boob enhancement, tackling myths, benefits, and expert advice to help potential candidates make informed decisions.

Pmoc Abrava: Supply, Pricing, and Quality Guide
This guide explains what “Pmoc Abrava” is used for in professional settings and how suppliers evaluate quality and consistency. It offers an objective overview of common procurement considerations, documentation, and verification practices. Readers will also find a comparison-style supplement section and practical requirements before choosing a source.
